
















A healthcare appointment scheduling app lives or dies on two things: how it models available time, and how it keeps patients from forgetting the booking. Everything else, from the patient-facing screens to the dashboards, sits on top of those two decisions.
This guide covers what to build, in what order, and where a project quietly gets more expensive than anyone planned. It's written for clinics, health startups and product owners comparing build options before they commit a budget.
What the scheduling data model has to represent
Availability and appointments are separate things, and your database should treat them that way. The HL7 FHIR standard makes the split explicit: a Slot resource is a block of time that may be open for booking, and it says nothing about the appointments placed into it.
Each slot belongs to one schedule, which covers a period such as a week. HL7's own example is a service offering eight one-hour appointments each weekday, which becomes one schedule and 40 slots. As patients book, the matching slots flip to busy.
That structure handles more than it first appears to. A slot can hold several appointments, which suits group sessions. It can be marked busy with no appointment attached, which is how you block a clinician's lunch. It can be reserved for walk-ins through its appointment type.
Two limits matter before you copy the model. Slots carry no recurrence information, so repeating availability has to be generated by your own code or by extensions. And the Slot resource is only at Trial Use maturity, so check which FHIR version your partner clinics' systems actually speak before you commit.
Features worth building first
Start with the loop a patient and a front desk both touch every day: search for an open time, book it, change it, get reminded. Anything beyond that is a second release.
- Patient booking, rescheduling and cancellation without a phone call
- A staff calendar showing the same slots, with the ability to block time
- Automated reminders by text, with a confirm or cancel reply
- A waitlist that offers a freed slot to the next patient
- Role-based access, so front-desk staff, clinicians and patients each see only what they should
The waitlist is the item teams skip and then regret, because a cancellation that nobody fills is an empty hour on the schedule. Building it later means reopening the booking logic you just finished.
Insurance checks, payment at booking and video visits all have real value. Each also pulls in a third-party integration and a new compliance question, so add them after the core loop is live and measured. If video is on your list, our breakdown of telemedicine app development cost covers what drives that part of the bill.
How reminders cut no-shows, and by how much
Reminders work, but the type matters and the evidence is thinner than vendor marketing suggests. A rapid systematic review in JAMIA covering eight studies from high-income countries compared several interventions against usual care.
| Intervention | Appointments studied | Median risk ratio for a no-show | Certainty |
|---|---|---|---|
| Text message reminder | 158,669 (one trial) | 0.91 | High |
| Phone call reminder | 4,959 (three trials) | 0.61 | Moderate |
| Patient navigator call | 4,425 (one trial) | 0.55 | Moderate |
A risk ratio of 0.91 means roughly nine no-shows for every ten you would otherwise have. A call brings it nearer to six. Texts are the cheap default to automate, while calls cost staff time for a larger effect.
The review carries its own warnings. Four of the seven randomised trials had a high risk of bias, the authors reported little on cost-effectiveness, and the results may not hold in low-income countries or paediatric settings. The same review found that text reminders may raise same-day cancellations, which is another reason the waitlist earns its place.
Our practical reading: build texting first, and design the app so a clinic can route high-risk appointments to a staff call instead. You don't need to build the calling yourself.
HIPAA and hosting decisions for a healthcare appointment scheduling app
If the app stores or processes patient information in the cloud, the hosting provider is part of your compliance chain. According to Hunton's summary of the 2016 HHS guidance, a covered entity or business associate may use a cloud provider for electronic protected health information only with a HIPAA-compliant business associate agreement in place.
That agreement has to require Security Rule safeguards and require the provider to report any security incident it learns about. Cloud providers are also directly liable under the Security Rule, so the obligation doesn't sit only with you.
The same summary notes that servers outside the United States are permitted, but the risks of the host country should be weighed. For a scheduling app, the practical checklist is short: sign the agreement before any real patient data touches a system, and include analytics, messaging and email tools in that review. A reminder service that sends appointment details is handling the same data your database is.
We go deeper on this in HIPAA compliant app development. The short version is that compliance decided at the architecture stage costs a design conversation, and compliance decided after launch costs a rebuild.
Integrating with the systems clinics already run

Photo by Polina Tankilevitch on Pexels
Most clinics will not abandon their existing records system for a new booking app. Your scheduler has to read and write to it, or it becomes a second calendar that staff reconcile by hand.
That's the argument for modelling your own data on a standard such as FHIR from day one, even if your first client uses something else. Translating a clean internal model into a clinic's format is a bounded job. Untangling a custom model after three clients is not.
Sketch the integration scope with the first clinic before design starts. Ask which system holds the master calendar, who is allowed to change it, and what happens when both sides edit the same slot at once.
Choosing who builds it
A scheduling app looks simple on a feature list and gets complicated at its edges: concurrent bookings, time zones, clinician leave, integrations and audit requirements. Those edges are where an experienced product team earns its fee.
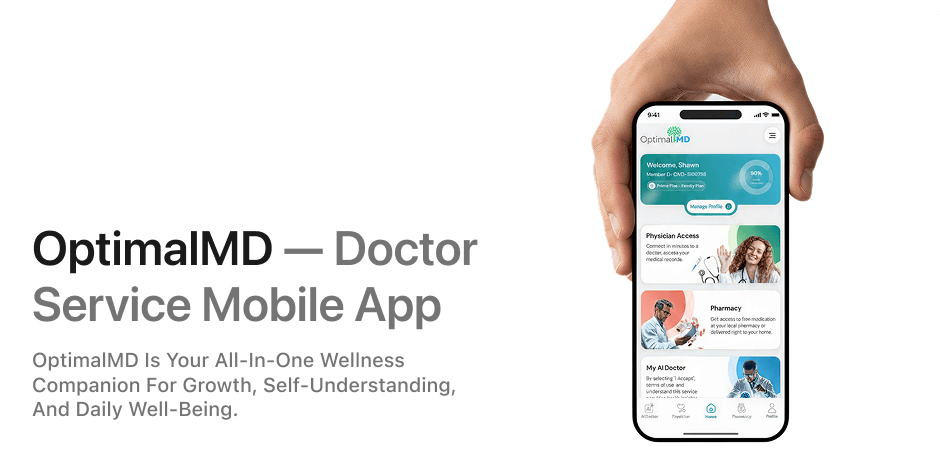
When we built OptimalMD's digital product, we handled design, development and launch end to end across the website, the members portal and the mobile app. Having one team own all three surfaces meant booking, accounts and the app shared one set of decisions.
If you're shortlisting partners, ask each to walk you through how they'd handle a double-booked slot and where patient data is stored. Our guide to choosing a healthcare app development company lists the other questions worth asking, and our apps and SaaS development team can scope a first release with you.
Launch with one clinic and measure two numbers
Ship to a single clinic or department first. Track the no-show rate before and after, and the share of bookings made without staff involvement.
Those two numbers tell you whether the reminders and self-service flow are working, and they decide what goes into the second release. A feature nobody has asked for yet can wait for the data.
Frequently asked questions
Do I need to use FHIR?
No law requires it for a scheduler, but it gives you a ready-made vocabulary for schedules, slots and appointments. It also makes integration with clinic systems easier to discuss.
Are text reminders enough to reduce no-shows?
They help, with high-certainty evidence from one large trial in the JAMIA review. Phone calls showed a larger effect in smaller trials, so a hybrid approach is worth planning for.
Does the hosting provider need to sign a business associate agreement?
Per the HHS guidance as summarised by Hunton, yes. A cloud provider that maintains patient health information needs a HIPAA-compliant agreement with you before it holds real data.
Should I launch with video visits and payments?
Start with booking, rescheduling and reminders. Each extra integration adds compliance review, so add them once the core loop is working.
Cover photo by Tessy Agbonome on Pexels
Sources
- Predictive model-based interventions to reduce outpatient no-shows: a rapid systematic review — JAMIA / PubMed Central
- FHIR R4 Slot resource — HL7 International





