
















The biggest healthcare mobile app trends of 2026 are being set by deadlines and billing rules rather than by gadgets. Payer APIs are due on January 1, 2027, and remote monitoring codes now pay for fewer days of data.
Meanwhile, investors no longer treat AI as a differentiator. Each of these changes what an app has to do before anyone downloads it.
Below, we sort the signals worth building around from the noise, and say which ones we'd act on first.
Healthcare mobile app trends with dates attached
Three regulatory and market changes carry fixed dates, which makes them easier to plan around than any forecast. The table lists them with what each one means for a product team.
| Date | What changes | Who it hits | What it means for an app |
|---|---|---|---|
| January 1, 2026 | Prior authorization decisions within 72 hours (urgent) or 7 calendar days (non-urgent); denials must give a specific reason | Medicare Advantage, Medicaid and CHIP plans, federal exchange issuers | Status screens can show a real decision window and a reason, not just "pending" |
| 2026 fee schedule | Device supply billable for 2 to 15 monitoring days in a 30-day period | Providers billing remote patient monitoring | Adherence features matter on day two, not day sixteen |
| January 1, 2027 | Patient Access, Provider Access and payer-to-payer APIs due | The same payer groups | Plan data becomes something an app can request instead of re-collect |
The prior authorization and API dates come from K&L Gates' summary of the CMS interoperability final rule. The monitoring change comes from the 2026 physician fee schedule, covered further down.
AI is now the baseline, not the pitch
Rock Health's first-half 2026 report put U.S. digital health funding at $7.4 billion across 244 deals, and it also stopped treating AI use as a distinguishing strategy because it has become so common. That's the more useful finding for anyone planning an app.
According to MedTech Dive's write-up of the July 17, 2026 report, Rock Health says AI has made more tailored implementations possible but also raised buyer expectations for measurable return. Investors, it adds, increasingly want founders with healthcare expertise.
Read that as a brief for your own product. A chatbot bolted onto a symptom checker doesn't earn a download anymore. A feature that shortens a specific task, with a number you can report to the clinic that bought it, does.
So pick one workflow where time is visibly lost, such as intake forms or message triage, and measure it before and after. That measurement is what buyers are now asking for.
Payer APIs will change how apps get patient data
Under the CMS rule, the Patient Access, Provider Access and payer-to-payer APIs are all due by January 1, 2027.
Patients get an opt-out for the provider API and an opt-in for the payer-to-payer one, and payers must offer a plain-language explanation of each.
The obligation sits with payers: Medicare Advantage organizations, state Medicaid and CHIP fee-for-service programs, Medicaid managed care plans, CHIP managed care entities and qualified health plan issuers on the federally facilitated exchanges. Providers and app builders aren't the ones on the hook.
But an app that today asks patients to type in insurance details, upload cards and chase referral status is working around a gap that is meant to close. Whether your product can use those APIs will depend on what your payers expose and how they let third parties connect, which the sources we read don't settle, so check that with each payer before you design around it.
Prior authorization is the nearer-term change. Since the start of 2026, covered payers must answer within 72 hours for urgent requests and seven calendar days for the rest. Drug authorizations are excluded for now, though CMS may extend the rules later.
For a patient-facing app, a status tracker that shows the clock and the stated reason for a denial is now buildable from real obligations rather than guesswork.
Remote patient monitoring now pays for shorter stretches
The 2026 physician fee schedule added CPT 99445, device supply for 2 to 15 monitoring days per 30-day period, reimbursed at the same rate as the older 99454. The old 16-day measurement requirement had been a barrier, and this code is meant to ease it.
The same rule created CPT 99470, time-based management for 10 to 19 minutes a month, paid at roughly half the 99457 rate. Physicians Practice's breakdown of the final rule, published November 5, 2025, is where those figures come from.
For app design, the shift moves the hard problem. Getting a patient to transmit readings for sixteen straight days used to decide whether a clinic got paid. Now a patient who gives you two days still counts, which makes onboarding and first-week reminders the screens worth the most polish.
One caution from the same article: the added flexibility doesn't loosen oversight. The OIG's August report flagged improper billing under physician NPIs, weak medical-necessity documentation and misuse of time-based management codes. An RPM app should log who reviewed what, and when, from the first release.
Security and compliance are the price of entry

Photo by DiePhotoPotato on Pexels
Every trend above multiplies the amount of protected data an app handles, whether it's plan records pulled through an API or device readings pushed from a patient's home. None of the sources we read changed the security rules themselves, so we'd treat this as a design constraint rather than a trend.
In practice that means deciding early which screens touch protected data, who can see each one, and how access gets logged. Retrofitting those answers after launch costs far more than asking the questions in the first sprint.
Our guides on what HIPAA-compliant app development actually takes and security best practices for healthcare apps cover the build-side detail. If audits are the worry, compliance software that keeps you audit-ready is the related read.
What we'd build first
With limited budget, we'd rank the work like this: the patient-facing status and onboarding flows first, because they lean on dated obligations; one measurable AI workflow second; payer data connections third, once you know what each payer exposes.
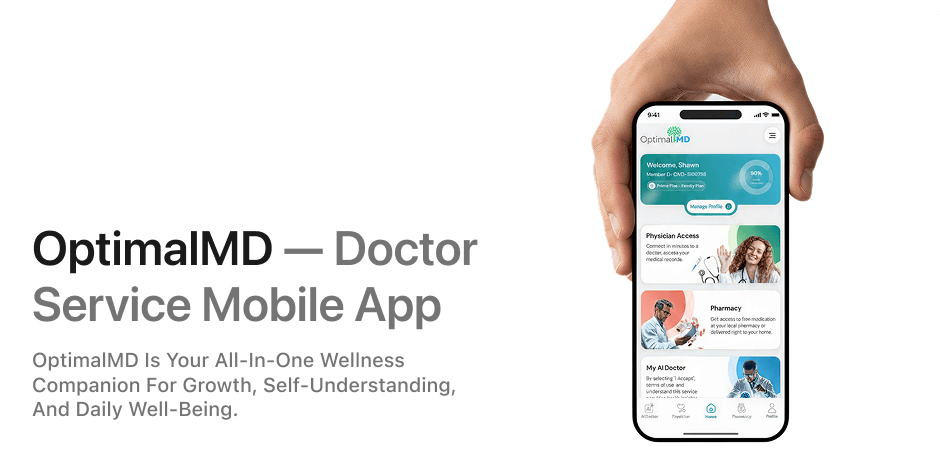
When we built OptimalMD's digital product, we handled design, development and launch for the website, the members portal and the mobile app, which is a reminder that these pieces have to share one data model from day one. You can read the details in the OptimalMD case study.
Cost is the usual next question, and it depends heavily on which of these features you include, as we break down in the real drivers of telemedicine app cost. If you're scoping a build, our apps and SaaS team works on exactly this kind of product.
Frequently asked questions
Does the CMS interoperability rule apply directly to healthcare apps?
No. The requirements fall on the listed payers, including Medicare Advantage organizations, Medicaid and CHIP programs and federal exchange issuers. An app is affected indirectly, through the data those payers will expose.
Are drug prior authorizations covered by the 72-hour and seven-day limits?
Not yet. Drugs are excluded for now, although CMS has said it may extend the rules later.
Do the new remote monitoring codes mean less compliance work?
No. The OIG's August report flagged improper billing, weak medical-necessity documentation and misuse of time-based management codes, so documentation matters as much as before.
Cover photo by TabTrader.com app on Pexels